Nursing Diagnosis and Nursing Intervention

Risk for Ineffective Airway Clearance - Goiter

Risk for ineffective airway clearance related to obstruction of the trachea, swelling, bleeding and laryngeal spasms

characterized by:
  • Subjective data: pain swallowing, painful wound.
  • Objective data: breathing fast and deep, there is a discharge / thick mucus in the throat, dyspnoe, stridor, cyanosis.
Goal to be achieved, according to the criteria of the results:
Maintaining a patent airway to prevent aspiration.

Plan of action / intervention:

1.) Monitor respiratory frequency, depth and breath work.
Rational:
Breathing normally sometimes quickly, but development of respiratory distress is indicative of tracheal compression due to edema or hemorrhage.

2.) Auscultation of breath sounds, record a voice Rhonchi.
Rational:
Rhonchi is indicative of obstruction laryngeal spasm that require rapid evaluation and intervention.

3.) Assess presence of dyspnea, stridor, and cyanosis. Note the sound quality.
Rational:
Indicators of tracheal obstruction / laryngeal spasm requiring immediate evaluation and intervention.

4.) Alert patients to avoid binding on the neck, supporting the head with a pillow.
Rational:
Decrease the likelihood of stress on the injured area for surgery.

5.) Assist in the change of position, deep breathing exercises and cough effectively or as indicated.
Rational:
Maintaining the cleanliness of the airway and evaluation. But the cough is not recommended and can cause severe pain, but it was necessary to clear the airway.

6.) Perform suctioning the mouth and trachea as indicated, note the color and characteristics of the sputum.
Rational:
Edema or pain can impair a patient's ability to issue and clear the airway itself.

7.) Perform reassessment of the regular cast, especially in the posterior.
Rational:
If there is bleeding, bandage the anterior part may seem dry because of blood deposited / collected in region-dependent.

8.) Investigate difficulty swallowing, accumulation of oral secretions.
Rational:
Is indicative of edema / hemorrhage frozen tissue surrounding the area of ​​operation.

9.) Maintain equipment near the patient's tracheostomy.
Rational:
Affected airway can create life-threatening emergency that requires action.

10.) Bone Surgery
Rational:
It might be very necessary for splicing / repair blood vessel bleeding continuously.

Activity Intolerance - Pneumonia

Activity Intolerance Nursing Diagnosis and Interventions - Pneumonia

Activity Intolerance related to imbalance between oxygen supply and demand, general weakness.

Goal: Report / show increased tolerance to activity.

Expected outcomes: No dipsnea, excessive weakness and vital signs within normal ranges.

Interventions:
a). Evaluate the client's response to the activity.
b). Provide quiet environment and limit visitors during the acute phase as indicated.
c). Explain the importance of rest in the treatment plan and the need to balance activity and rest
d). Help clients choose a comfortable position weeks to rest / sleep
e). Help the client care activities as needed.

Nursing Interventions Deficient Fluid and Electrolyte Volume - DHF

Nursing Diagnosis Care Plan for DHF: Deficient Fluid and Electrolyte Volume related to increased capillary permebilitas, bleeding

Goal: After nursing actions, balanced electrolyte fluid volume

Expected outcomes:
  • Showed improved fluid balance, evidenced by adequate urine output with normal specific gravity.
  • Vital signs are stable.
  • Moist mucous membranes, good turgor and capillary refill quickly.
Nursing Intervention for DHF: Deficient Fluid and Electrolyte Volume:

1. Monitor vital signs: compare with previous results.
Rationale: Changes in blood pressure and pulse can be used for a rough estimate blood loss.

2. Note the individual patient's physiological response to hemorrhage such mental changes, weakness, restlessness, anxiety, pallor, increased temperature and sweating.
Rational: symptomatology can be useful in measuring the weight / length episodes of bleeding, worsening of symptoms can indicate bleeding or inadequate understanding of the fluid.

3. Measure CVP when there
Rationale: Shows the circulating volume and cardiac responses to hemorrhage and fluid replacement, for example, CVP between 5 and 20 cm H2O showed adequate volume.

4. Supervise the input and output, and relationship to changes in weight, measuring blood loss / fluid through vomiting and defecation.

5. Maintain accurate records subtotal fluid / blood during replacement therapy.
Rationale: Potential excess fluid transfusion up, especially when the extra volume of blood transfusions given before.

6. Maintain bed rest: prevents vomiting and defecation current voltage.
Rationale: Activities / vomiting increased intra-abdominal pressure and can trigger bleeding continued.

7. Observations of secondary hemorrhage, such as nose / gum bleeding continuously from the area of ​​injection.
Rationale: Loss / inadequate replacement clotting factors can trigger the occurrence of KID.

8. Give fluid / blood as indicated.
Rationale: Fluid replacement depends on the degree of hypovolemia and length of bleeding.

9. Full of fresh blood / red cell packaging
Rational: full of fresh blood indicated for acute bleeding (with shock), due to deficiency of blood clotting factors deposits.

10. Fresh frozen plasma (FFP) and / or platelets
Rational: coagulation factors / components decimation by 2 mechanisms: loss of bleeding and clotting.

11. Record intake and output
Rationale: Measuring inputs and expenditures can see fluid volume deficit occurs.

12. Check the hemoglobin, hematocrit, platelets every 4-6 hours
Rational: Seeing bleeding conditions change.

Nursing Management for Diarrhea

Nursing Management for Diarrhea

Diarrhea is often caused an extraordinary event, such as the number of cholera patients a lot in a short time. But with the management of diarrhea fast, precise and quality, mortality can be reduced to a minimum.

Problem Formulation
  1. What Definition of Diarrhea?
  2. What Etiology of Diarrhea?
  3. How Pathophysiology of Diarrhea?
  4. What Are the Clinical Symptoms of Diarrhea?
  5. What are the Complications of Diarrhea?
  6. How Nursing Care Plan of Diarrhea?
Purpose
  1. Knowing the Definition of Diarrhea.
  2. Knowing the etiology of diarrhea.
  3. Knowing the pathophysiology of diarrhea.
  4. Know the Clinical Symptoms Diarrhea.
  5. Knowing the Complications of diarrhea.
  6. Knowing Nursing diarrhea.

Pathophysiology and Clinical Manifestation of Appendicitis

Pathophysiology and Clinical Manifestation of Appendicitis

Pathophysiology of Appendicitis

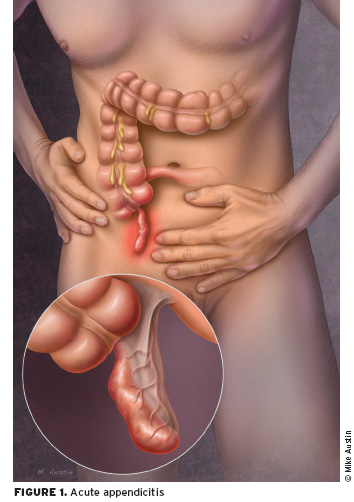
Appendix inflamed and had edema as a result of congestion, possibly by fecalith (hard mass of feces), tumor or a foreign object. Inflammatory process, increased intraluminal pressure that will impede lymph flow resulting in edema, diapedesis bacteria and ulceration of the mucosa cause upper abdominal pain or severe diffuse progressively, within a few hours, localized to the right lower quadrant of the abdomen. Finally, the inflamed appendix contains pus.

When mucus secretion continues, the pressure will continue to rise causing widespread inflammation and the resulting local peritoneum, causing pain under the right side is called acute suppurative appendicitis. If then the flow will be disrupted arterial wall infarction followed by a gangrenous appendix called gangrenous appendicitis. If the walls are already fragile perforated appendicitis rupture will occur. If all of the above process is slow, omentum and adjacent bowel will move toward an appendix to arise a local mass dsebut appendicular infiltrates. Inflammation of the appendix may be an abscess or disappear.

In children, shorter omentum and appendix are longer, thinner wall of the appendix. The situation is coupled with immune system becomes less ease of perforation. In older people perforation easily happen because there is an interruption of blood vessels (Mansjoer, 2000).

Clinical Manifestations of Appendicitis
  • Lower quadrant pain
  • Mild fever
  • Nausea and vomiting
  • Loss of appetite
  • Local tenderness at the point mc Burney
  • Tenderness off (or intesifikasi result of pain when pressure is released)
  • Signs rovsing can arise by doing palpoasi lower left quadrant which paradoksimal cause pain felt in the lower right quadrant
  • Abdominal distension due to paralytic ileus
  • The patient's condition deteriorates

Nursing Diagnosis Decreased Cardiac Output for Hyperthyroidism

Decreased Cardiac Output related to uncontrolled hyperthyroidism, hypermetabolism, increased cardiac workload.

Patients objective / evaluation criteria;
  • Maintain adequate cardiac output according to the needs of the body

characterized by:
  • Stable vital signs,
  • normal peripheral pulses,
  • normal capillary refill,
  • good mental status,
  • no dysrhythmias

Nursing Intervention:

Independent
  • Monitor vital signs. Note the magnitude of the pressure pulse.
  • Check / meticulous possibility complained of chest pain patients.
  • Assess pulse / heart rate while the patient sleeps.
  • Auscultation of heart sounds, note the extra heart sounds, a gallop rhythm and a systolic murmur.
  • ECG monitor, record or note rate or in cardiac rhythm and the presence of dysrhythmias
  • Observation of signs and symptoms of severe thirst, dry mucous membranes, weak pulse, slow capillary refill, decreased urine output, and hypotension
  • Note adnya history of asthma / bronkokontriksi, pregnancy, sinus bradycardia / heart block progress to heart failure
Collaboration
  • Give fluids through IV as indicated
  • Give medications as indicated:
  • Monitor the results of lab tests: serum potassium, serum calcium, sputum culture
  • Perform regular ECG monitoring
  • Give oxygen as indicated
  • Prepare for surgery

Meningitis Definition, Etiology and Clinical Manifestations

Definition of Meningitis

Meningitis is inflammation of the meninges (the membranes that surround the brain and spinal cord) and is caused by a virus, bacteria or fungus organs (Smeltzer, 2001).

Meningitis is an infection of the fluid of the brain with inflammatory piamater, arachnoid and in a milder degree of the brain and spinal cord tissues were superficial. (Neurology capita selekta, 1996)

Meningitis is an inflammation of the arachnoid and pia mater (lepto meningens) of the brain and spinal cord. Bacteria and viruses are the most common cause of meningitis, although fungi can also cause. Bacterial meningitis is more common. Early detection and treatment will give more better results according to Revelation Widagdo et al (2008:105)

Etiology of Meningitis

Meningitis caused by a virus is generally harmless, will recover without specific treatment and care. But bacterial meningitis can lead to serious conditions, such as brain damage, hearing loss, lack of ability to learn, can even cause death. While meningitis is caused by a fungus is very rare, this type generally affects people with damaged immune (immune system) as in patients with AIDS.

Bacteria that can cause meningitis attack include:
1. Streptococcus pneumoniae (pneumococcus).
These bacteria are the most common cause of meningitis in infants or children. This type of bacteria can also cause pneumonia, ear and nasal cavity (sinus).

2. Neisseria meningitidis (meningococcus).
This bacterium is the second most after Streptococcus pneumoniae meningitis caused by an infection of the upper respiratory tract and then the bacteria enter the bloodstream.

3. Haemophilus influenzae (Haemophilus).
Haemophilus influenzae type b (Hib) is a type of bacteria that can also cause meningitis. This type of virus as the cause upper respiratory infections, middle ear and sinuses. Vaccine (Hib vaccine) has shown a decrease in the number of cases of meningitis caused by these bacteria.

4. Listeria monocytogenes (listeria).
This is one type of bacteria that can cause meningitis. These bacteria can be found in many places, in the dust and in contaminated food. Food is usually a type of cheese, hot dogs and bacon sandwich which is derived from the bacterium local animal (pet).

5. Other bacteria that can also cause meningitis are Staphylococcus aureus and Mycobacterium tuberculosis.

Clinical Manifestations of Meningitis
  • Early in the disease, fatigue, changes in power to remember, change in behavior
  • In accordance with the rapid course of the disease the patient becomes stuporous
  • Headache
  • Sore muscle pain
  • Pupillary reaction to light. Photofobia when light is directed at the patient's eye.
  • Dysfunction of the nerves III, IV, VI
  • Motor movement at the beginning of the disease is usually normal and common in the advanced stages of hemiparesis, hemiplagia, and decreased muscle tone
  • Reflex positive Brudzinski and Kernig reflex
  • Nausea
  • Vomiting
  • Tachycardia
  • Convulsions
  • Patients feel fear and anxiety

Risk for Injury - Nursing Care Plan Meningitis


Nursing Diagnosis for Meningitis: Risk for Injury related to general weakness.

The expected outcomes / evaluation criteria pediatric patients: No seizures or comorbidities or other injury.

intervention
a. Monitor the spasms / twitching of the hands, feet and mouth or other facial muscles.
Rational: reflecting on the CNS in general irritation that require immediate evaluation and possible intervention to prevent complications.

b. Provide security for patients by providing assistance on the bed and keep the barrier remained in place and attach the plastic artificial airway or soft rolls and a suction bulb.
Rationale: protect patients when seizures. Note; enter the airway assistance / soft rolls if only jaw relaxation, not forced to enter as his teeth shut and soft tissue will be damaged.

c. Maintain bed rest during the acute phase. Move. Moving with the help of corresponding improvement in the situation.
Rational: reducing the risk of falls / trauma case vertigo, syncope or ataxia.

d. Give medication as indicated as phenytoin (Dilantin), diazepam, phenobarbital.
Rational: an indication for the treatment and prevention of seizures. Records: Phenobarbital may cause respiratory and sedative defresi and mask the signs / symptoms of increased ICP.

Retropharyngeal Abscess Prevention and Treatment

Retropharyngeal abscess Prevention and Treatment

Definition of retropharyngeal abscess

Retrofaringeal abscess is a pus accumulation in the back of the throat tissues.

Cause of retropharyngeal abscess
  • Abscesses are usually caused by streptococcal infection from the tonsils, throat, sinuses, adenoids, nasal or middle ear.
  • Sometimes an injury to the back of the throat caused by thorn fish can also cause abscesses retrofaringeal.
  • Although rare, retrofaringel abscess can also be caused by tuberculosis.
  • Retrofaringeal abscess usually affects children aged less than 5 years.
  • Networking on the back of the throat allows the formation of children's cavity containing pus (which this does not occur in adults).
  • Infection in these areas can occur during or shortly after by a bacterial throat infection.

Symptoms of retropharyngeal abscess

Symptoms include:
  • History of sore throat, nasal infection or tooth abscess
  • High fever
  • Severe sore throat
  • Swollen neck lymph nodes
  • Difficulty swallowing
  • Salivating
  • Respiratory Disorders
  • Intercostal retraction (withdrawal of muscles between the ribs when people try so hard to breathe)
  • Stridor (harsh breathing sound).

Complications of retropharyngeal abscess
  • Bleeding around the abscess
  • Rupture of the abscess into the airways (which can cause airway obstruction)
  • Pneumonia
  • The spread of infection to the chest.
Diagnosis of retropharyngeal abscess
  • Diagnosis is based on symptoms and physical examination.
  • X-rays or a CT scan of the neck showed a cavity containing pus between the throat and cervical spine.
  • Blood tests showed an increase in the number of white blood cells.
  • Breeding throat mucus can indicate the presence of the causative organism.

Treatment of retropharyngeal abscess
  • To overcome infection drainage surgery (to remove the pus) and high doses of antibiotics given intravenously.

Prevention of retropharyngeal abscess
  • Diagnosis and treatment in pharyngitis and nasopharyngeal infection usually can prevent abscess retrofaringeal.

Physical Examination, Laboratory, and Radiology for Acute Appendicitis

Physical Examination, Laboratory, and Radiology for Acute Appendicitis

There are several tests that can be performed by a medical team to determine and diagnose the presence of Appendicitis by patients. Among them is the physical examination, laboratory tests and radiology examinations:

1. Physical Examination of Acute Appendicitis

Physical Examination of Acute Appendicitis

In acute appendicitis, the observation would seem the swelling of the abdominal cavity which seemed to tighten the abdominal wall (distended). On palpation of the right lower abdominal area, often when pressed will feel pain when pressure is released and also will feel pain (Blumberg sign), which is the key to the diagnosis of acute appendicitis.

By the action of the right leg bent and thighs strong / leg high in the lift, the abdominal pain is getting worse. Suspicion of an inflammation of the appendix is ​​enhanced when an anal or vaginal and cause pain as well. Rectal temperature (rectal) temperatures are higher than the armpits, over longer support the existence of appendicitis.

2. Laboratory Examination of Acute Appendicitis

In laboratory tests of blood, which can be found is an increase of white blood cells (leukocytes) to about 10,000 - 18.000/mm3. If an increase is more than that, then it is likely the appendix had been perforated (ruptured).

3. Radiological Examination of Acute Appendicitis

Radiological Examination of Acute Appendicitis

Plain abdomen may show a fecalith. However, this examination is rarely helpful in diagnosing appendicitis. Ultrasonography (USG) is quite helpful in the diagnosis of appendicitis enforcement (71-97%), especially for pregnant women and children. The highest level of accuracy is by CT scan (93-98%). With a CT scan can be seen clearly picture the appendix.
Copyright © Nursing Diagnosis Intervention. All rights reserved. Template by CB | Published By Kaizen Template | GWFL | KThemes